
DOSING & ADMINISTRATION OF BEXLUTRY

SAME DOSING SCHEDULE AND ADMINISTRATION
BEXLUTRY FITS SEAMLESSLY INTO YOUR WORKFLOW
BEXLUTRY is an IV injection of lutetium Lu 177 dotatate1
Dosing schedule of BEXLUTRY
- BEXLUTRY contains 370 MBq/mL (10 mCi/mL) of lutetium Lu 177 dotatate at the time of calibration
- Administer 7.4 GBq (200 mCi) every 8 weeks (±1 week) for a total of 4 doses


Before each dose of BEXLUTRY

*Administer long-acting octreotide 30 mg intramuscularly (IM) between 4 and 24 hours after each dose of BEXLUTRY. Do not administer long-acting octreotide within 4 weeks prior to each subsequent dose of BEXLUTRY.
†Continue long-acting octreotide 30 mg IM every 4 weeks after completing BEXLUTRY until disease progression or for 18 months following treatment initiation, at the discretion of a physician.
Day of administration considerations1
Recommended timing for the administration of premedications, concomitant medications, and BEXLUTRY
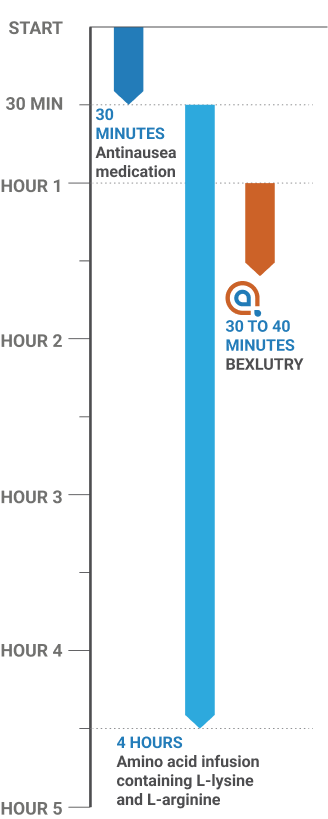

Administer amino acid solution containing L-lysine and L-arginine intravenously 30 minutes before administering BEXLUTRY. Continue the infusion during and for at least 3 hours after the infusion of BEXLUTRY. Do not decrease the dose of the amino acid solution if the dose of BEXLUTRY is reduced.

PREFER TO HAVE INSTRUCTIONS ON HAND?
Access the administration guide for easy future reference.
Safe handling of BEXLUTRY

PROPER TECHNIQUE1
- Use aseptic technique and shielding when handling BEXLUTRY
- Use tongs when handling the vial

INSPECTION1
- Inspect the vial through a shielded window for particulate matter and discoloration

DOSE VERIFICATION
- Verify activity using a radioactivity dose calibrator1
- Using the radioactivity dose calibrator, ensure BEXLUTRY dose is the correct activity per written directive for the correct patient1,2
- Ensure expiration/BUD is documented according to the label and administration occurs before that time1,3

PROPER DISPOSAL
- Dispose radiopharmaceutical waste as required by law and institutional SOPs1
- Minimize storage demands with Curium’s lead safe retrieval service
Abbreviations
BUD, beyond-use date; SOP, standard operating procedure.
Monitoring for adverse events
The administered activity of BEXLUTRY should be modified based on hematologic, renal, hepatic, hypersensitivity, and other adverse reactions.1
KEY MONITORING DURING TREATMENT1
- Hematologic: Complete blood count with differential before each dose; signs of bone marrow suppression
- Renal: Serum creatinine and calculated creatinine clearance prior to each dose; signs of renal dysfunction
- Hepatic: Transaminases, bilirubin, serum albumin, and international normalized ratio during treatment; signs of hepatic impairment
- Hypersensitivity*: During infusion and ≥2 hours after for signs of allergic reaction; have emergency medications/supplies available
- Neuroendocrine hormonal crisis*: During infusion and shortly after for signs of hormonal release (flushing, diarrhea, hypotension, bronchoconstriction)
STOP BEXLUTRY INFUSION IMMEDIATELY IF
- Severe hypersensitivity occurs1
- Carcinoid crisis develops4†

Withhold, reduce dose, or permanently discontinue based on severity of adverse reactions.1 Please see full Prescribing Information.
*Other common grade 3-4 infusion reactions include nausea, vomiting, and electrolyte changes.1
†A patient in carcinoid crisis requires the immediate administration of an IV bolus of octreotide as needed until stabilized. Alert the intensive care unit, monitor vital signs, and consider supportive care.4
Need more information about preparation and administration?
Our Clinical Care Guide and Administration Guide are designed to support your staff.
IMPORTANT SAFETY INFORMATION
WARNINGS AND PRECAUTIONS
-
Risk From Radiation Exposure: Bexlutry contributes to a patient’s overall long-term cumulative radiation exposure. Long-term cumulative radiation exposure is associated with an increased risk for cancer. These risks of radiation associated with the use of Bexlutry are greater in pediatric patients than in adults.
Radiation can be detected in the urine for up to 30 days following Bexlutry administration. Minimize radiation exposure to patients, medical personnel, and household contacts during and after treatment with Bexlutry consistent with institutional good radiation safety practices, patient management procedures, Nuclear Regulatory Commission patient-release guidance, and instructions to the patient for follow-up radiation protection at home.
-
Myelosuppression: In NETTER-1, myelosuppression occurred more frequently in patients receiving lutetium Lu 177 dotatate injection with long-acting octreotide compared to patients receiving high-dose long-acting octreotide (all Grades/Grade 3 or 4): anemia (81%/0) versus (54%/1%); thrombocytopenia (53%/1%) versus (17%/0); and neutropenia (26%/3%) versus (11%/0). In NETTER-1, platelet nadir occurred at a median of 5.1 months following the first dose. Of the 59 patients who developed thrombocytopenia, 68% had platelet recovery to baseline or normal levels. The median time to platelet recovery was 2 months. Fifteen of the nineteen patients in whom platelet recovery was not documented had post-nadir platelet counts. Among these 15 patients, 5 improved to Grade 1, 9 to Grade 2, and 1 to Grade 3. Monitor blood cell counts. Withhold dose, reduce dose, or permanently discontinue Bexlutry based on the severity of myelosuppression.
-
Secondary Myelodysplastic Syndrome (MDS) and Leukemia: In NETTER-1, with a median follow-up time of 76 months in the main study, myelodysplastic syndrome (MDS) was reported in 2.3% of patients receiving lutetium Lu 177 dotatate injection with long-acting octreotide compared to no patients receiving high-dose long-acting octreotide.
In ERASMUS, 16 patients (2.0%) developed MDS and 4 (0.5%) developed acute leukemia. The median time to onset was 29 months (9 to 45 months) for MDS and 55 months (32 to 125 months) for acute leukemia.
-
Renal Toxicity: In ERASMUS, 8 patients (< 1%) developed renal failure 3 to 36 months following lutetium Lu 177 dotatate injection. Two of these patients had underlying renal impairment or risk factors for renal failure (e.g., diabetes or hypertension) and required dialysis.
Administer the recommended amino acid solution before, during and after Bexlutry to decrease the reabsorption of lutetium Lu 177 dotatate through the proximal tubules and decrease the radiation dose to the kidneys. Advise patients to hydrate and to urinate frequently before, on the day of, and the day after administration of Bexlutry.
Monitor serum creatinine and calculated creatinine clearance. Withhold dose, reduce dose, or permanently discontinue Bexlutry based on the severity of renal toxicity.
Patients with baseline renal impairment may be at increased risk of toxicity due to increased radiation exposure.
-
Hepatotoxicity: In ERASMUS, 2 patients (< 1%) were reported to have hepatic tumor hemorrhage, edema, or necrosis, with one patient experiencing intrahepatic congestion and cholestasis. Patients with hepatic metastasis may be at increased risk of hepatotoxicity due to radiation exposure.
Monitor transaminases, bilirubin, serum albumin, and international normalized ratio (INR) during treatment. Withhold dose, reduce dose, or permanently discontinue Bexlutry based on the severity of hepatotoxicity.
-
Hypersensitivity Reactions: Hypersensitivity reactions, including angioedema, occurred in patients treated with lutetium Lu 177 dotatate injection. Monitor patients closely for signs and symptoms of hypersensitivity reactions, including anaphylaxis, during and following Bexlutry administration for a minimum of 2 hours in a setting where cardiopulmonary resuscitation medication and equipment are available. Discontinue the infusion upon the first observation of any signs or symptoms consistent with a severe hypersensitivity reaction and initiate appropriate therapy.
Premedicate patients with a history of Grade 1 or 2 hypersensitivity reactions to Bexlutry before subsequent doses. Permanently discontinue Bexlutry in patients who experience Grade 3 or 4 hypersensitivity reactions.
-
Neuroendocrine Hormonal Crisis: Neuroendocrine hormonal crises, manifesting with flushing, diarrhea, bronchospasm and hypotension, occurred in < 1% of patients in ERASMUS and typically occurred during or within 24 hours following the initial lutetium Lu 177 dotatate injection dose. Two (< 1%) patients were reported to have hypercalcemia. Monitor patients for flushing, diarrhea, hypotension, bronchoconstriction or other signs and symptoms of tumor-related hormonal release. Administer intravenous somatostatin analogs, fluids, corticosteroids, and electrolytes as indicated.
-
Embryo-Fetal Toxicity: Based on its mechanism of action, Bexlutry can cause fetal harm when administered to a pregnant woman. Verify pregnancy status of females of reproductive potential prior to initiating Bexlutry. Advise pregnant women of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with Bexlutry and for 7 months after the last dose. Advise males with female partners of reproductive potential to use effective contraception during treatment with Bexlutry and for 4 months after the last dose.
-
Risk of Infertility: Bexlutry may cause infertility in males and females. The recommended cumulative dose of 29.6 GBq of Bexlutry results in a radiation absorbed dose to the testes and ovaries within the range where temporary or permanent infertility can be expected following external beam radiotherapy.
ADVERSE REACTIONS
The most common Grade 3-4 adverse reactions (≥ 4% with a higher incidence in lutetium Lu 177 dotatate injection arm) reported in NETTER-1 were lymphopenia, increased GGT, vomiting, nausea, increased AST, increased ALT, hyperglycemia and hypokalemia.
With a median follow-up time of more than 4 years, the following rates of serious adverse reactions were reported in ERASMUS: myelodysplastic syndrome (2%), acute leukemia (1%), renal failure (2%), hypotension (1%), cardiac failure (2%), myocardial infarction (1%), and neuroendocrine hormonal crisis (1%).
DRUG INTERACTIONS
Somatostatin Analogs: Somatostatin and its analogs competitively bind to somatostatin receptors and may interfere with the efficacy of Bexlutry. Discontinue long-acting somatostatin analogs at least 4 weeks and short-acting octreotide at least 24 hours prior to each Bexlutry dose. Administer short- and long-acting octreotide during Bexlutry treatment as recommended.
Glucocorticoids: Glucocorticoids can induce down-regulation of subtype 2 somatostatin receptors (SSTR2). Avoid repeated administration of high doses of glucocorticoids during treatment with Bexlutry.
USE IN SPECIFIC POPULATIONS
Lactation
Advise women not to breastfeed during treatment with Bexlutry and for 2.5 months after the last dose.
Pediatric Use
Somatostatin Receptor-Positive Gastroenteropancreatic Neuroendocrine Tumors: The risks of radiation exposure associated with Bexlutry are greater in pediatric patients than in adult patients due to longer life expectancy. The safety and effectiveness of Bexlutry have not been established in pediatric patients younger than 12 years old with somatostatin receptor-positive GEP-NETs.
Pediatric use information is approved for Advanced Accelerator Applications USA INC’s LUTATHERA (lutetium Lu 177 dotatate) injection for intravenous use. However, due to Advanced Accelerator Applications USA Inc.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
LUTATHERA® is a registered trademark of Advanced Accelerator Applications International SA.
INDICATIONS AND USAGE
Bexlutry™ (lutetium Lu 177 dotatate injection) is indicated for the treatment of adults with somatostatin receptor-positive gastroenteropancreatic neuroendocrine tumors (GEP-NETs), including foregut, midgut, and hindgut neuroendocrine tumors.
References
- BEXLUTRY. Prescribing information. Curium US LLC; 2026.
- Code of Federal Regulations. Title 10–Energy, Chapter I–Nuclear Regulatory Commission, Part 35–Medical Use of Byproduct Material, Subpart B–General Administrative Requirements, CFR §35.40. National Archives. Accessed June 4, 2026. https://www.ecfr.gov/current/title-10/chapter-I/part-35/subpart-B/section-35.40
- Hosono M, Ikebuchi H, Nakamura Y, et al. Manual on the proper use of lutetium-177-labeled somatostatin analogue (Lu-177-DOTA-TATE) injectable in radionuclide therapy (2nd ed.). Ann Nucl Med. 2018;32(3):217-235. doi:10.1007/s12149-018-1230-7
- Laudicella R, Faggiano A, Pirro V, et al. AIMN, ITANET, SIE joint position paper for the recognition, prevention and management of NET carcinoid syndrome and crises during peptide receptor radionuclide therapy. Eur J Nucl Med Mol Imaging. 2026;53(3):1445-1457. doi:10.1007/s00259-025-07596-2