
EFFICACY OF BEXLUTRY


SAME CLINICAL DATA
FDA APPROVAL OF BEXLUTRY LEVERAGED ESTABLISHED CLINICAL OUTCOMES FROM THE REFERENCE Lu 177 DOTATATE THERAPY1-3
BEXLUTRY demonstrated chemical, biological, and targeting characteristics comparable to the reference radioligand therapy (RLT) through the US Food and Drug Administration's (FDA's) 505(b)(2) pathway,1-4 with efficacy and safety supported by clinical trials of the reference RLT.1,3
Lutetium Lu 177 dotatate + SSA for second-line (2L) therapy5
NETTER-1 study design: A pivotal, phase 3, randomized, open-label, multicenter study1,5,6
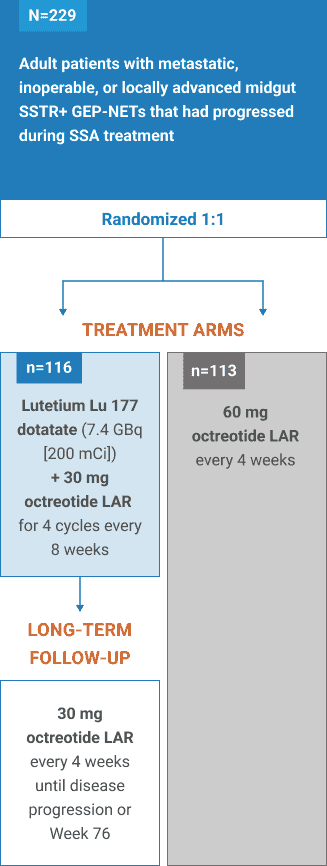
PRIMARY ENDPOINT
Progression-free survival (PFS)*
*As assessed by independent central review according to RECIST v1.1 by radiologists unaware of the treatment, defined as the time from randomization to documented disease progression or death from any cause.
SECONDARY ENDPOINTS
ORR, OS, DoR, safety
Select inclusion criteria:
- Well-differentiated grade 1 or 2 tumors
- Ki-67 index ≤20%
- Karnofsky PS ≥60
- Treatment with octreotide LAR (20 or 30 mg) for ≥12 weeks prior to randomization
Select exclusion criteria:
- Treatment with >30 mg octreotide LAR <12 weeks before randomization
- Prior treatment with RLT
- Prior EBRT to >25% of the bone marrow
- Any surgery, radioembolization, chemoembolization, chemotherapy, and/or radiofrequency ablation ≤12 weeks before randomization
Stratification factors:
- SSTR uptake: grade 2, 3, or 4
- Time receiving constant dose of octreotide: ≤6 months vs >6 months
Primary analysis: Statistically significant improvement in PFS1†
- Median PFS was not reached with lutetium Lu 177 dotatate + SSA (95% CI: 18.4-NE) vs 8.5 months with SSA alone (95% CI: 6.0-9.1)
Long-term post hoc PFS analysis (centrally assessed): Lutetium Lu 177 dotatate + SSA demonstrated >2-year PFS in patients being treated with second-line therapy7‡
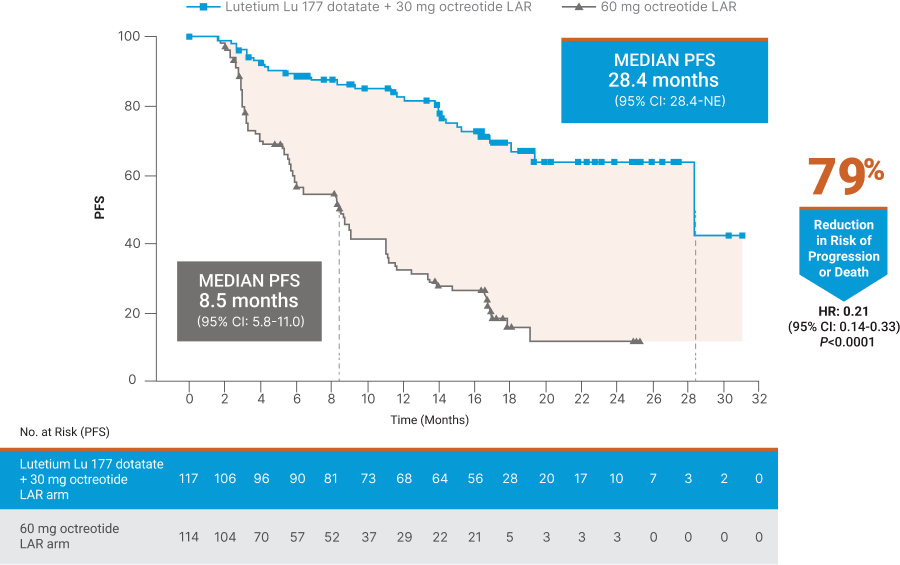
- In a post hoc final analysis by investigators, median PFS was 25.0 months with lutetium Lu 177 dotatate + SSA vs 8.5 months with SSA alone (HR, 0.30 [95% CI: 0.21-0.44]; P<0.0001)7§
- The updated PFS analyses are based on post hoc assessments conducted on a subgroup of the NETTER-1 study after the prespecified primary analysis7 and are observational only. They were not powered for statistical significance and the results should be interpreted with caution
†Median duration of follow-up was 14 months and the cutoff date for analysis was July 24, 2015.5
‡Cutoff date for analysis was August 31, 2017.7
§Cutoff date for final analysis was January 18, 2021.7
Abbreviations
CI, confidence interval; DoR, duration of response; EBRT, external beam radiation therapy; GEP-NET, gastroenteropancreatic neuroendocrine tumor; HR, hazard ratio; LAR, long-acting release; NE, not evaluated; ORR, objective response rate; OS, overall survival; PS, performance status; RECIST, Response Evaluation Criteria in Solid Tumors; SSA, somatostatin analog; SSTR, somatostatin receptor; SSTR+, SSTR-positive.
Lutetium Lu 177 dotatate + SSA for first-line therapy8
NETTER-2 study design: A phase 3, randomized, open-label, multicenter study8,9
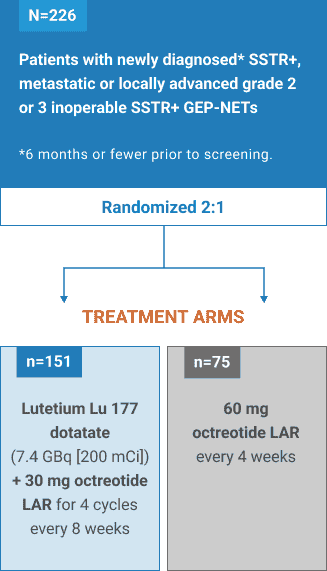
PRIMARY ENDPOINT
PFS†
†Centrally assessed by RECIST v1.1 and defined as the time from randomization to first documented progression or death due to any cause.
SECONDARY ENDPOINTS
ORR, OS, TTD in select QoL scales, DCR, DoR, safety
Select inclusion criteria:
- Well-differentiated grade 2 or 3 tumors
- Ki-67 index ≥10% and ≤55%
- Karnofsky PS ≥60
Select exclusion criteria:
- Documented RECIST progression to previous treatments for the current GEP-NET
- Prior treatment with RLT
- Prior EBRT to >25% of the bone marrow
- Any previous systemic therapy for GEP-NETs administered for >1 month or ≤12 weeks prior to randomization
- Any previous radioembolization, chemoembolization, and/or radiofrequency ablation for GEP-NETs
- Surgery ≤12 weeks prior to randomization
Stratification factors:
- Tumor grade: grade 2 vs grade 3
- Site of origin: pancreatic NET vs other primary tumor site
Primary analysis: Statistically significant improvement in PFS for newly diagnosed patients with grade 2 or 3 GEP-NETs8
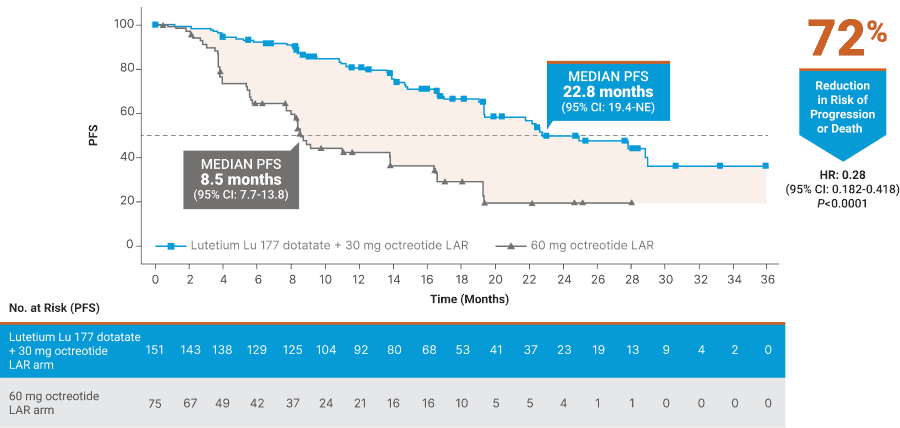
Adapted from The Lancet, Vol. 403, Singh S, Halperin D, Myrehaug S, et al. [177Lu]Lu-DOTA-TATE plus long-acting octreotide versus high-dose long-acting octreotide for the treatment of newly diagnosed, advanced grade 2-3, well-differentiated, gastroenteropancreatic neuroendocrine tumours (NETTER-2): an open-label, randomised, phase 3 study, pages 2807-2817, Copyright 2024, with permission from Elsevier.
- Median duration of follow-up: 23.2 months (from randomization to cutoff date)
- The primary PFS analysis data cutoff was July 20, 2023
Abbreviations
DCR, disease control rate; NET, neuroendocrine tumor; QoL, quality of life; TTD, time to deterioration.
ERASMUS study design1
ERASMUS was a phase 1/2, single-institution, single-arm, open-label trial. Patients (N=1214) with inoperable SSTR+ tumors received lutetium Lu 177 dotatate through an expanded access program at a single site in the Netherlands. Lutetium Lu 177 dotatate 7.4 GBq (200 mCi) was administered every 6 to 13 weeks for up to 4 cycles, with concurrent amino acid solution.
A retrospective review of medical records was conducted to document serious adverse reactions in a subset of 811 patients. The median follow-up was >4 years.1
Safety profile
Explore the well-established safety profile, supported by the clinical trials of the reference RLT.
IMPORTANT SAFETY INFORMATION
WARNINGS AND PRECAUTIONS
-
Risk From Radiation Exposure: Bexlutry contributes to a patient’s overall long-term cumulative radiation exposure. Long-term cumulative radiation exposure is associated with an increased risk for cancer. These risks of radiation associated with the use of Bexlutry are greater in pediatric patients than in adults.
Radiation can be detected in the urine for up to 30 days following Bexlutry administration. Minimize radiation exposure to patients, medical personnel, and household contacts during and after treatment with Bexlutry consistent with institutional good radiation safety practices, patient management procedures, Nuclear Regulatory Commission patient-release guidance, and instructions to the patient for follow-up radiation protection at home.
-
Myelosuppression: In NETTER-1, myelosuppression occurred more frequently in patients receiving lutetium Lu 177 dotatate injection with long-acting octreotide compared to patients receiving high-dose long-acting octreotide (all Grades/Grade 3 or 4): anemia (81%/0) versus (54%/1%); thrombocytopenia (53%/1%) versus (17%/0); and neutropenia (26%/3%) versus (11%/0). In NETTER-1, platelet nadir occurred at a median of 5.1 months following the first dose. Of the 59 patients who developed thrombocytopenia, 68% had platelet recovery to baseline or normal levels. The median time to platelet recovery was 2 months. Fifteen of the nineteen patients in whom platelet recovery was not documented had post-nadir platelet counts. Among these 15 patients, 5 improved to Grade 1, 9 to Grade 2, and 1 to Grade 3. Monitor blood cell counts. Withhold dose, reduce dose, or permanently discontinue Bexlutry based on the severity of myelosuppression.
-
Secondary Myelodysplastic Syndrome (MDS) and Leukemia: In NETTER-1, with a median follow-up time of 76 months in the main study, myelodysplastic syndrome (MDS) was reported in 2.3% of patients receiving lutetium Lu 177 dotatate injection with long-acting octreotide compared to no patients receiving high-dose long-acting octreotide.
In ERASMUS, 16 patients (2.0%) developed MDS and 4 (0.5%) developed acute leukemia. The median time to onset was 29 months (9 to 45 months) for MDS and 55 months (32 to 125 months) for acute leukemia.
-
Renal Toxicity: In ERASMUS, 8 patients (< 1%) developed renal failure 3 to 36 months following lutetium Lu 177 dotatate injection. Two of these patients had underlying renal impairment or risk factors for renal failure (e.g., diabetes or hypertension) and required dialysis.
Administer the recommended amino acid solution before, during and after Bexlutry to decrease the reabsorption of lutetium Lu 177 dotatate through the proximal tubules and decrease the radiation dose to the kidneys. Advise patients to hydrate and to urinate frequently before, on the day of, and the day after administration of Bexlutry.
Monitor serum creatinine and calculated creatinine clearance. Withhold dose, reduce dose, or permanently discontinue Bexlutry based on the severity of renal toxicity.
Patients with baseline renal impairment may be at increased risk of toxicity due to increased radiation exposure.
-
Hepatotoxicity: In ERASMUS, 2 patients (< 1%) were reported to have hepatic tumor hemorrhage, edema, or necrosis, with one patient experiencing intrahepatic congestion and cholestasis. Patients with hepatic metastasis may be at increased risk of hepatotoxicity due to radiation exposure.
Monitor transaminases, bilirubin, serum albumin, and international normalized ratio (INR) during treatment. Withhold dose, reduce dose, or permanently discontinue Bexlutry based on the severity of hepatotoxicity.
-
Hypersensitivity Reactions: Hypersensitivity reactions, including angioedema, occurred in patients treated with lutetium Lu 177 dotatate injection. Monitor patients closely for signs and symptoms of hypersensitivity reactions, including anaphylaxis, during and following Bexlutry administration for a minimum of 2 hours in a setting where cardiopulmonary resuscitation medication and equipment are available. Discontinue the infusion upon the first observation of any signs or symptoms consistent with a severe hypersensitivity reaction and initiate appropriate therapy.
Premedicate patients with a history of Grade 1 or 2 hypersensitivity reactions to Bexlutry before subsequent doses. Permanently discontinue Bexlutry in patients who experience Grade 3 or 4 hypersensitivity reactions.
-
Neuroendocrine Hormonal Crisis: Neuroendocrine hormonal crises, manifesting with flushing, diarrhea, bronchospasm and hypotension, occurred in < 1% of patients in ERASMUS and typically occurred during or within 24 hours following the initial lutetium Lu 177 dotatate injection dose. Two (< 1%) patients were reported to have hypercalcemia. Monitor patients for flushing, diarrhea, hypotension, bronchoconstriction or other signs and symptoms of tumor-related hormonal release. Administer intravenous somatostatin analogs, fluids, corticosteroids, and electrolytes as indicated.
-
Embryo-Fetal Toxicity: Based on its mechanism of action, Bexlutry can cause fetal harm when administered to a pregnant woman. Verify pregnancy status of females of reproductive potential prior to initiating Bexlutry. Advise pregnant women of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with Bexlutry and for 7 months after the last dose. Advise males with female partners of reproductive potential to use effective contraception during treatment with Bexlutry and for 4 months after the last dose.
-
Risk of Infertility: Bexlutry may cause infertility in males and females. The recommended cumulative dose of 29.6 GBq of Bexlutry results in a radiation absorbed dose to the testes and ovaries within the range where temporary or permanent infertility can be expected following external beam radiotherapy.
ADVERSE REACTIONS
The most common Grade 3-4 adverse reactions (≥ 4% with a higher incidence in lutetium Lu 177 dotatate injection arm) reported in NETTER-1 were lymphopenia, increased GGT, vomiting, nausea, increased AST, increased ALT, hyperglycemia and hypokalemia.
With a median follow-up time of more than 4 years, the following rates of serious adverse reactions were reported in ERASMUS: myelodysplastic syndrome (2%), acute leukemia (1%), renal failure (2%), hypotension (1%), cardiac failure (2%), myocardial infarction (1%), and neuroendocrine hormonal crisis (1%).
DRUG INTERACTIONS
Somatostatin Analogs: Somatostatin and its analogs competitively bind to somatostatin receptors and may interfere with the efficacy of Bexlutry. Discontinue long-acting somatostatin analogs at least 4 weeks and short-acting octreotide at least 24 hours prior to each Bexlutry dose. Administer short- and long-acting octreotide during Bexlutry treatment as recommended.
Glucocorticoids: Glucocorticoids can induce down-regulation of subtype 2 somatostatin receptors (SSTR2). Avoid repeated administration of high doses of glucocorticoids during treatment with Bexlutry.
USE IN SPECIFIC POPULATIONS
Lactation
Advise women not to breastfeed during treatment with Bexlutry and for 2.5 months after the last dose.
Pediatric Use
Somatostatin Receptor-Positive Gastroenteropancreatic Neuroendocrine Tumors: The risks of radiation exposure associated with Bexlutry are greater in pediatric patients than in adult patients due to longer life expectancy. The safety and effectiveness of Bexlutry have not been established in pediatric patients younger than 12 years old with somatostatin receptor-positive GEP-NETs.
Pediatric use information is approved for Advanced Accelerator Applications USA INC’s LUTATHERA (lutetium Lu 177 dotatate) injection for intravenous use. However, due to Advanced Accelerator Applications USA Inc.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
LUTATHERA® is a registered trademark of Advanced Accelerator Applications International SA.
INDICATIONS AND USAGE
Bexlutry™ (lutetium Lu 177 dotatate injection) is indicated for the treatment of adults with somatostatin receptor-positive gastroenteropancreatic neuroendocrine tumors (GEP-NETs), including foregut, midgut, and hindgut neuroendocrine tumors.
References
- BEXLUTRY. Prescribing information. Curium US LLC; 2026.
- US Food and Drug Administration. Approved Drug Products With Therapeutic Equivalence Evaluations. 44th ed. 2024. Accessed April 13, 2026. https://www.fda.gov/drugs/drug-approvals-and-databases/approved-drug-products-therapeutic-equivalence-evaluations-orange-book
- Lutathera. Prescribing information. Advanced Accelerator Applications USA Inc; 2024.
- Data on file. Curium US LLC.
- Strosberg J, El-Haddad G, Wolin E, et al; NETTER-1 trial investigators. Phase 3 trial of 177Lu-dotatate for midgut neuroendocrine tumors. N Engl J Med. 2017;376(2):125-135. doi:10.1056/
NEJMoa1607427 - A study comparing treatment with 177Lu-DOTA0-Tyr3-Octreotate to octreotide LAR in patients with inoperable, progressive, somatostatin receptor positive midgut carcinoid tumours (NETTER-1). ClinicalTrials.gov ID: NCT01578239. National Library of Medicine. Accessed May 1, 2026. https://clinicaltrials.gov/study/NCT01578239?term=NCT01578239&viewType=Card&rank=1
- Kunz PL, Benson AB, Bodei L, et al. The phase 3 NETTER-1 study of 177Lu-DOTATATE in patients with midgut neuroendocrine tumours: updated progression-free survival analyses. Presented at: North American Neuroendocrine Tumor Society (NANETS) Annual Multidisciplinary Medical Symposium; November 4-6, 2021; Chicago, IL.
- Singh S, Halperin D, Myrehaug S, et al; NETTER-2 trial investigators. [177Lu]Lu-DOTA-TATE plus long-acting octreotide versus high-dose long-acting octreotide for the treatment of newly diagnosed, advanced grade 2-3, well-differentiated, gastroenteropancreatic neuroendocrine tumours (NETTER-2): an open-label, randomised, phase 3 study. Lancet. 2024;403(10446):2807-2817. doi:10.1016/S0140-6736(24)00701-3
- Study to evaluate the efficacy and safety of Lutathera in patients with grade 2 and grade 3 advanced GEP-NET (NETTER-2). ClinicalTrials.gov ID: NCT03972488. National Library of Medicine. Accessed May 1, 2026. https://clinicaltrials.gov/study/NCT03972488?tab=study